
Case study 01
Centrova
An AI clinical research platform that took screening a patient for a trial from about 90 minutes to 5–10, without taking the decision away from the researcher.
The problem
Clinical trial recruitment is quietly failing the people it’s meant to help.
Miss rate
80%
of clinical trials fail to meet their initial enrollment timelines, costing pharma millions per day in opportunity cost alone.
Termination cause
57%
of clinical trial terminations are due to enrollment difficulties. The research just stops.
Behind these numbers are delayed cures, patients who lose access to life-saving treatments, and drug costs that rise to cover inefficient research. Clinical staff burn out under inefficiencies that ripple across the whole ecosystem.
Research and mandate
I was brought in to understand a space the previous design lead couldn’t.
Clinical research has its own language, its own conventions, and workflows that are entrenched for good reason. You can’t parachute in and start designing. I interviewed clinical researchers, PIs, site coordinators and monitors across all kinds of institutions, accounting for blinding protocols, randomization structures, cohort configurations, and how things change when the sponsor is a major CRO like IQVIA or a more in-house operation.
The complexity wasn’t just in the features. It was in knowing which edge cases were universal enough to design for, and which were site-specific customizations. Getting that wrong would have produced a tool that worked for one workflow and failed everyone else.
The platform
One platform. Every stakeholder in the trial process.
SmartMatch
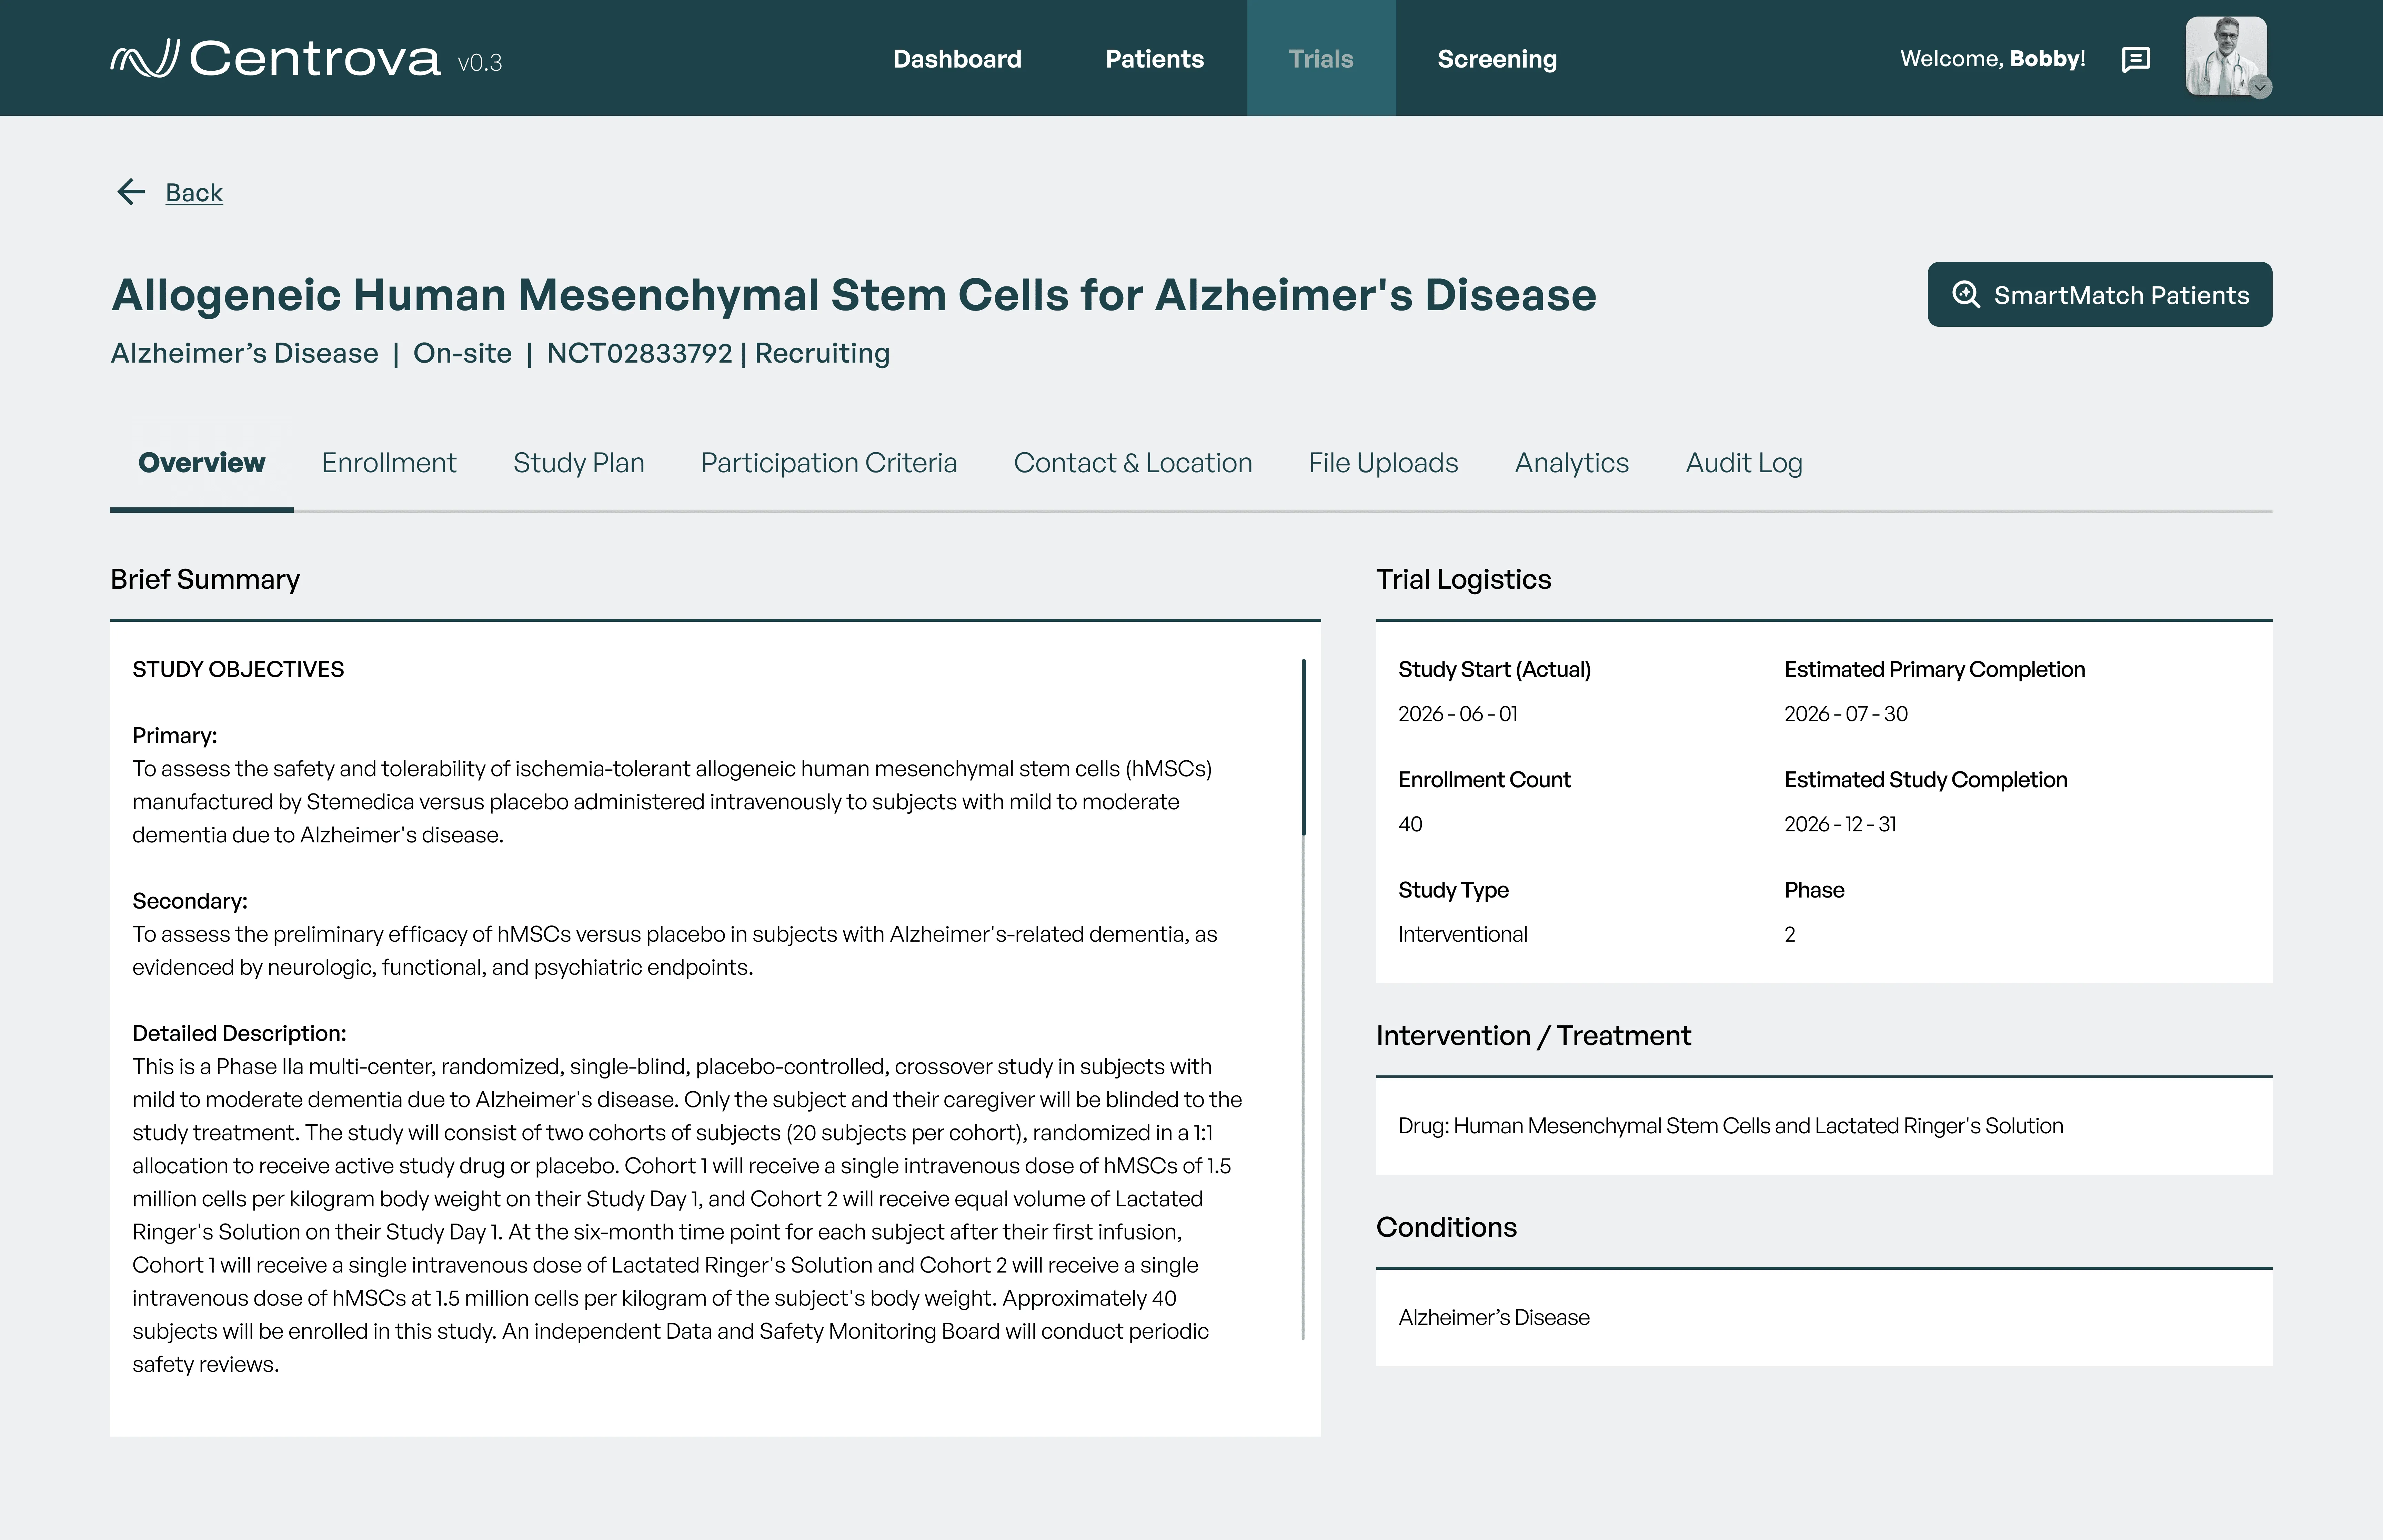
Bidirectional matching: the right patients for a trial, or the right trials for a patient.
AI Screening
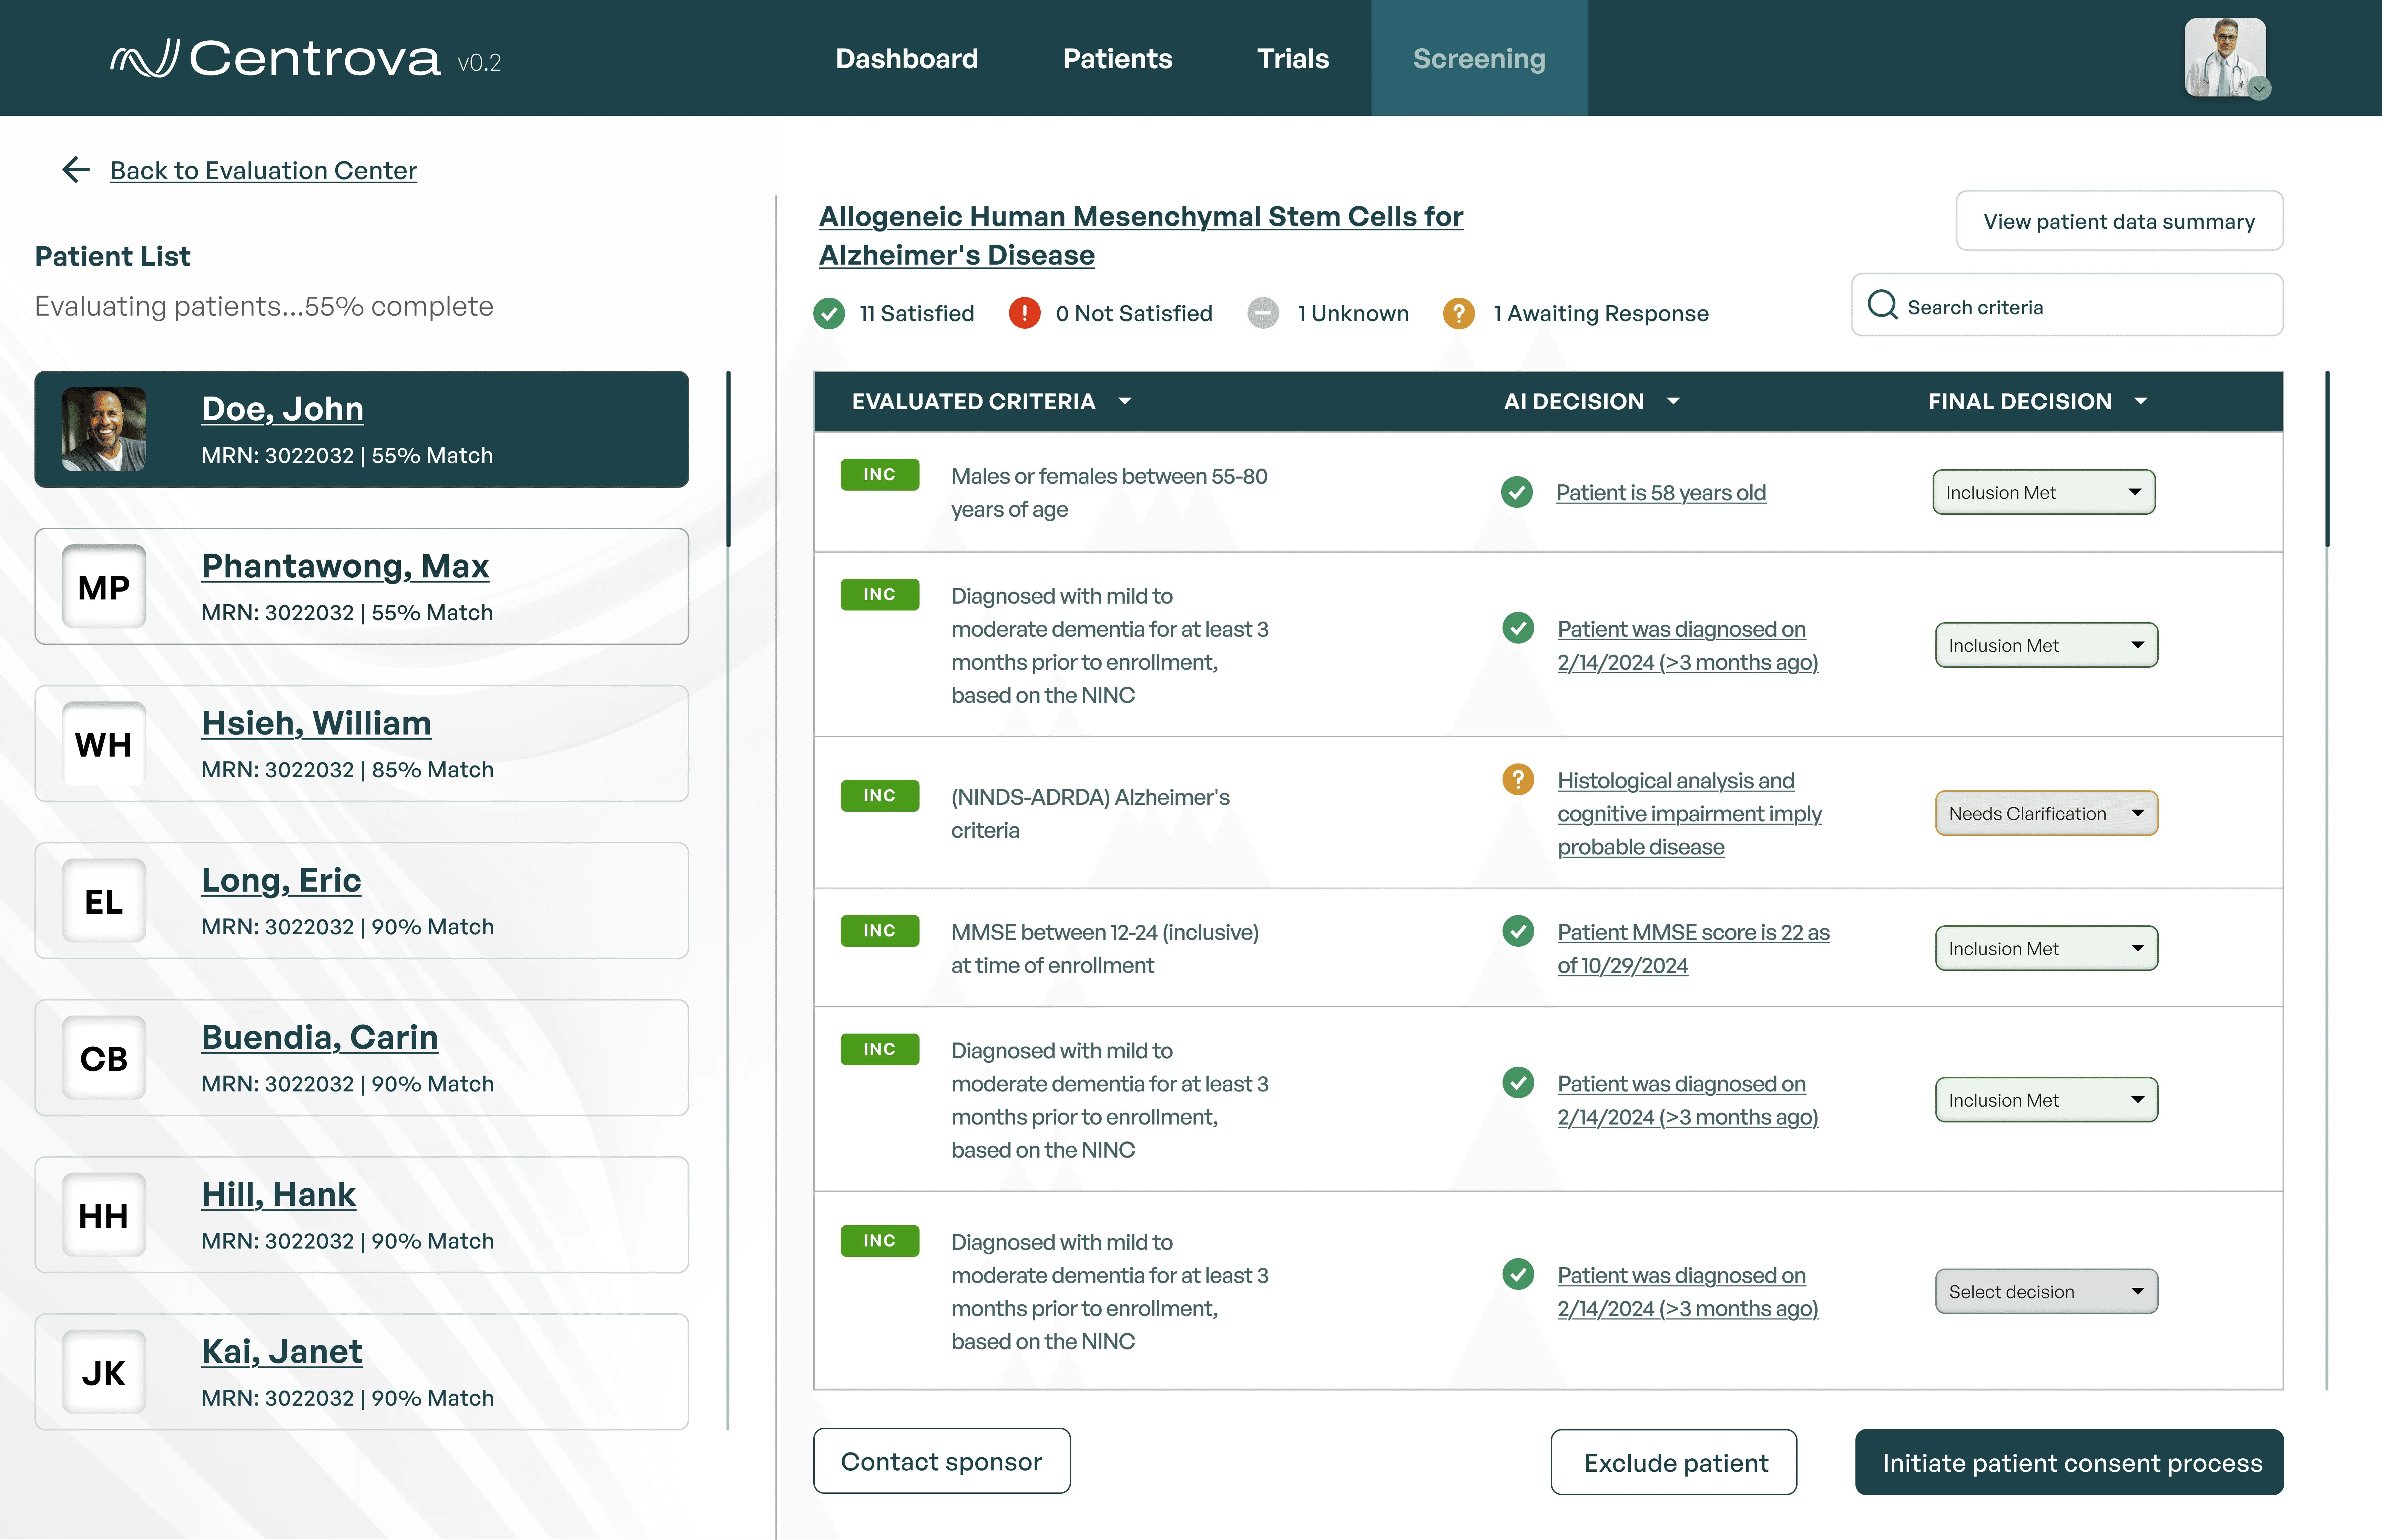
Bulk patient–trial evaluation. Every recommendation shows the exact line from the patient file behind it.
Trial Manager
Role-based access, double-blind support, enrollment tracking and direct criteria editing.
Data Hub
Shared storage for visit data, trial documents and deviation logs. One-click export to sponsors.
Clinical Teams
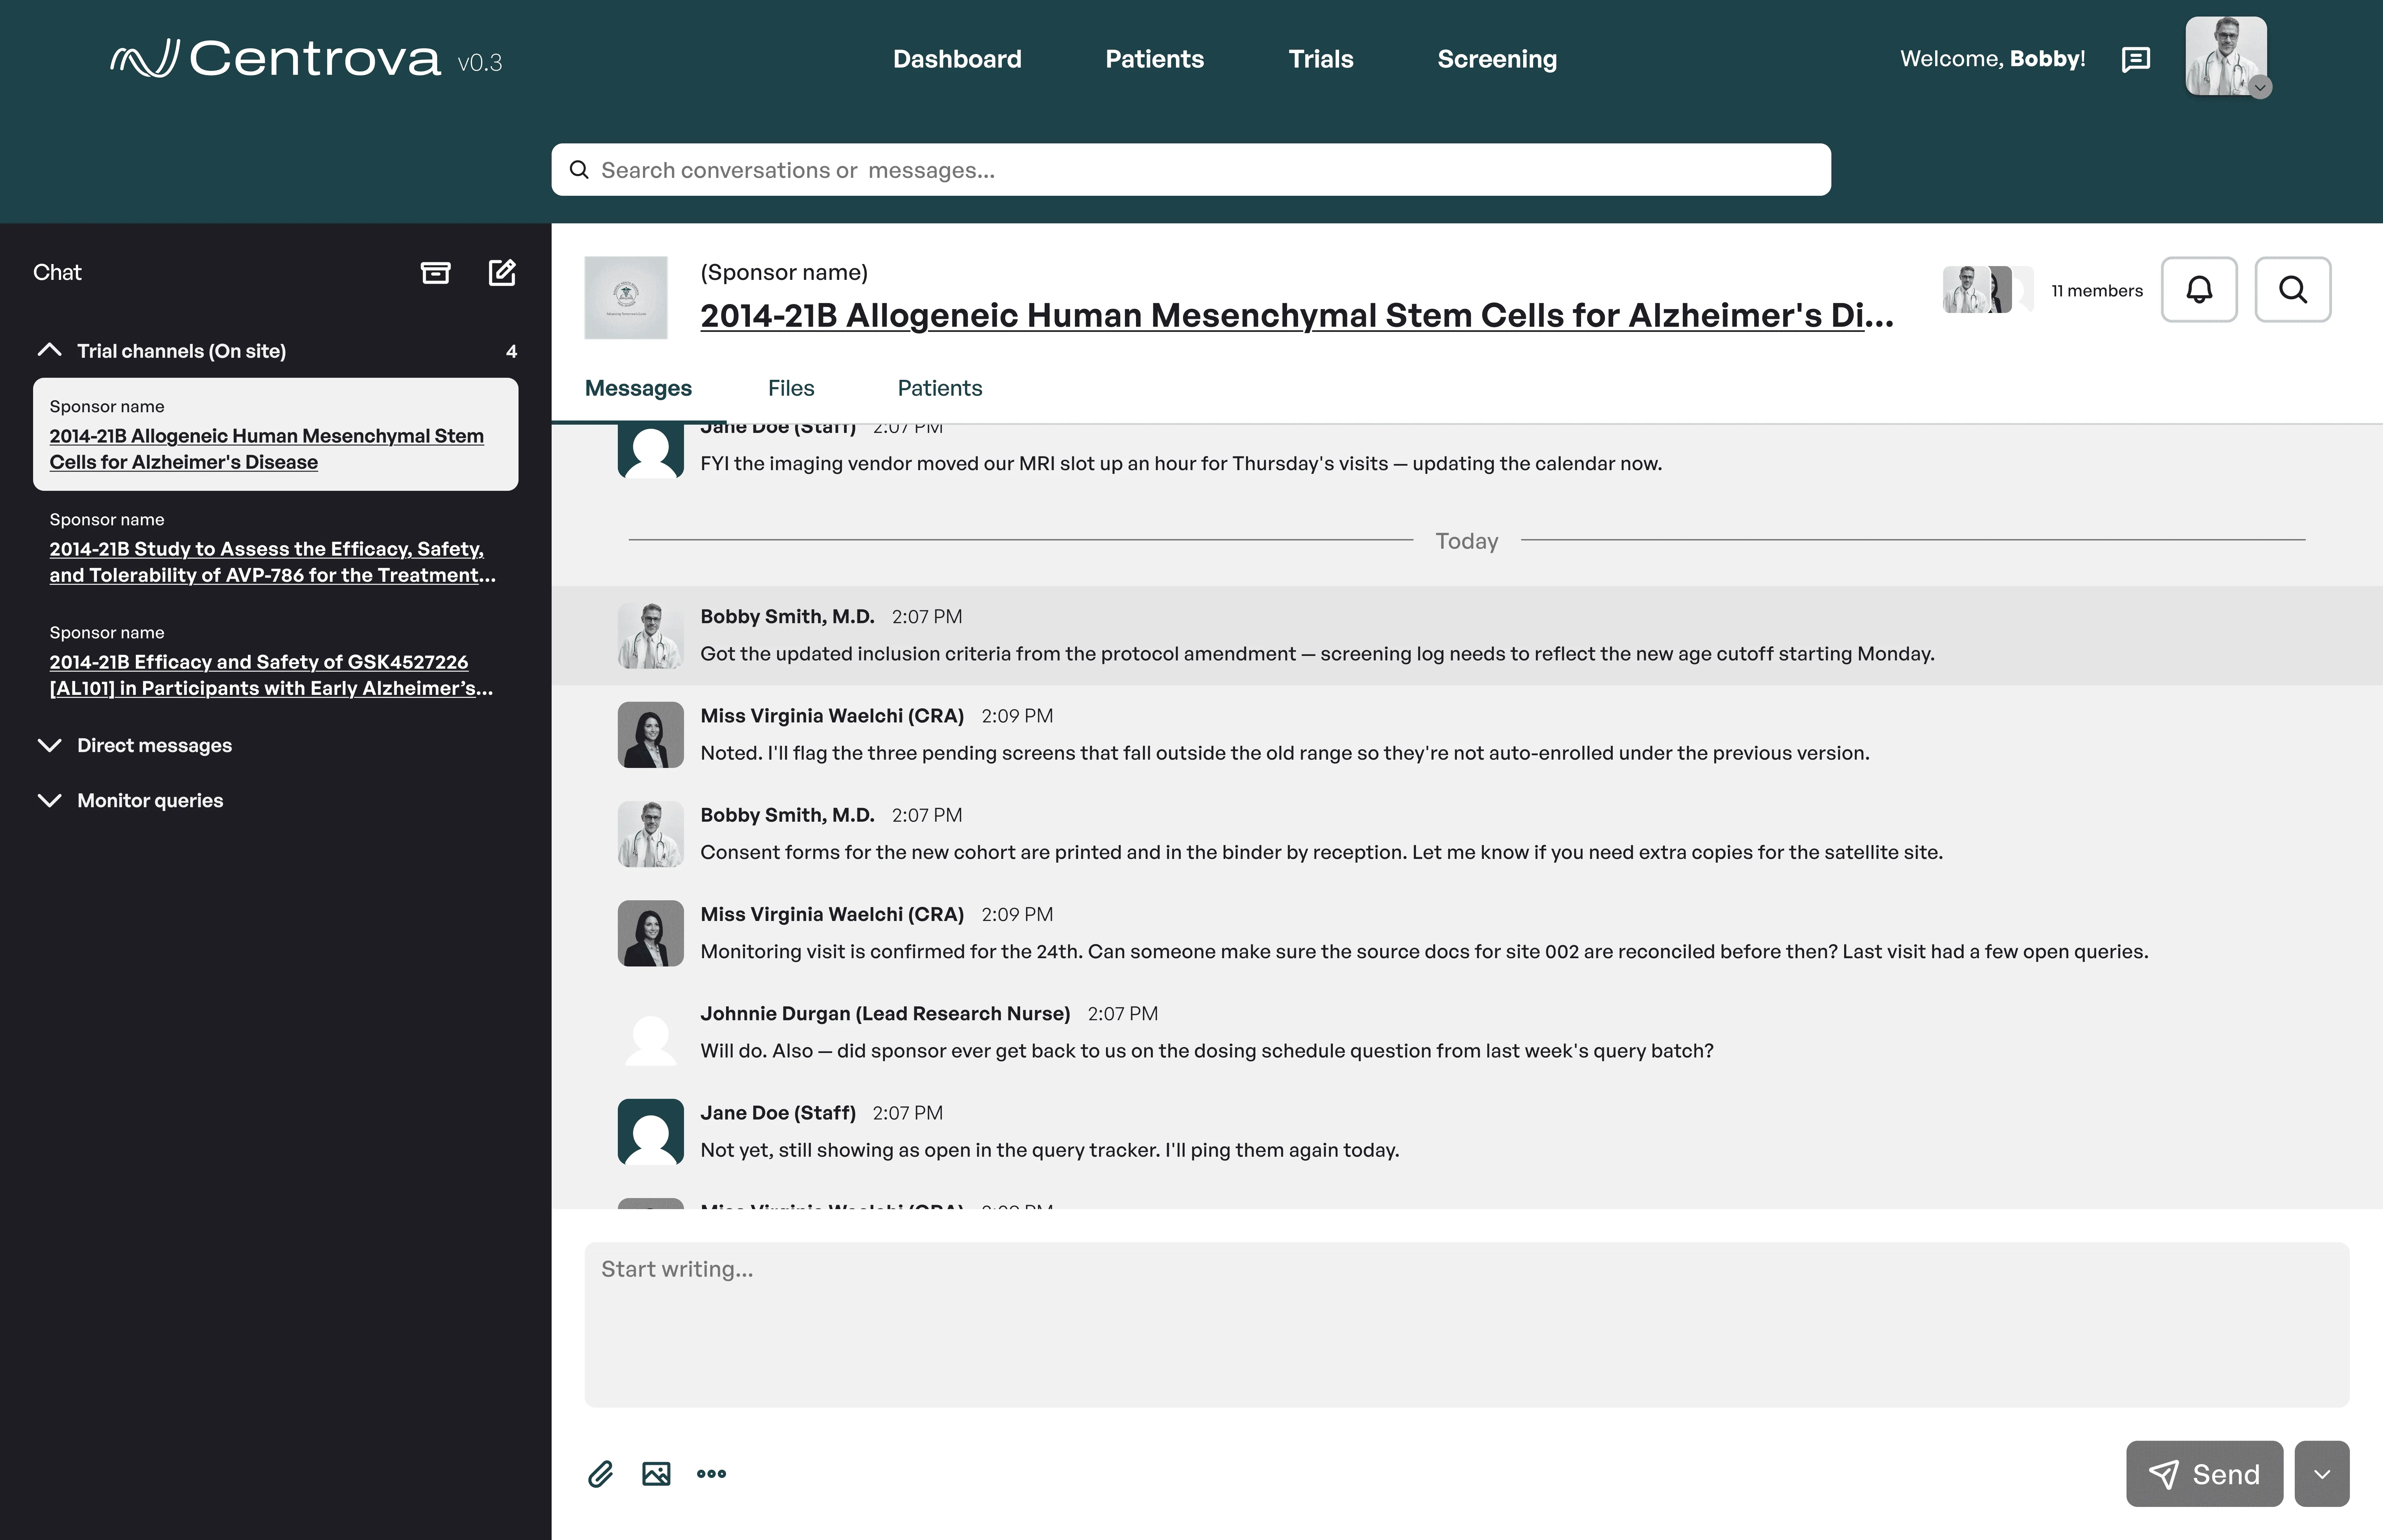
Trial channels and monitor-to-site lines, with separate blinded and unblinded chats.
Monitor Portal
Monitors review evaluations and request documents without a remote visit or a single e-mail.
Sites currently patch this together with 2–3 tools that weren’t built for each other. What makes Centrova different is that all of it exists together.
Key design decisions
The hardest problems weren’t visual. They were structural.
01 Adding monitors to the platform
Monitors and sites work on the same trials but share information through e-mail chains, phone calls and remote visits. Centrova holds patient data relevant to screening without being an EHR, so it can give monitors the access they need, de-identified and HIPAA-compliant.
I took this to the CEO and COO with the interview data behind it. It was outside the original scope. They got on board, and it became one of the features monitors responded to most positively in the pilot.
02 Redesigning the screening flow
My first approach was a wizard: select a patient, select a trial, run the evaluation. Clean, simple, and wrong. Research showed four real workflows (one-to-one, bulk-to-one, one-to-many, bulk-to-many), and the wizard locked researchers out of adding evaluations mid-session when a patient arrived unexpectedly. The Screening Center replaced it.
03 AI transparency, human authority
The AI screens every selected patient against every criterion at once, and each decision links to the exact line in the patient’s file it used. Researchers make the final call on each criterion. The AI recommends. The human decides. That’s a trust decision and a compliance one: clinical responsibility stays with qualified staff.
04 Research-focused, not clinical
Researchers don’t see themselves as hospital administrators, and in high-stakes settings a flashy AI look reduces trust. Large type, top navigation, content front and center.
Outcomes
From 90 minutes to 5–10, and one place for every stakeholder.
| Measure | Before | With Centrova |
|---|---|---|
| Time per screening evaluation | ~90 minutes | 5–10 minutes |
| Monitor-to-site communication | E-mail, phone, remote visits | Unified in-platform |
| Software tools required | 2–3 disconnected tools | 1 integrated platform |
| Eligibility documentation | Manual, inconsistent | Auto-generated PDF |
An order-of-magnitude change makes bulk screening of large patient populations feasible for the first time without scaling staff to match. Pilot monitors described the centralization as dramatically simpler than their current multi-tool workflow.
Reflection
The most impactful thing I did wasn’t a screen.
It was the research that led me to push for monitors in the platform. That changed the product’s scope and its value proposition, and it came from listening closely enough to find a problem the original brief hadn’t accounted for.
The screening redesign taught me that simplicity isn’t the absence of features. It’s the right structure for the features you have.